Pain administration looks deceptively easy from the exterior. Give an analgesic, reassess, discharge. In actual method, it is just one of one of the most nuanced components of nursing. Clients arrive strained with concern, complicated comorbidities, polypharmacy, and a history that might consist of opioid dependancy or undertreated discomfort. You manage physiology, regulation, paperwork, and human feeling, often under time pressure. That is the context for PUAEME008, the Australian system of expertise that concentrates on providing pain relief in emergency and pre-hospital settings. If you are considering discomfort management courses, aiming for a discomfort monitoring certification, or choosing short programs hurting administration to hone your side, it pays to understand what this unit covers and exactly how to transform it into day-to-day competence.
What PUAEME008 in fact means in practice
PUAEME008 is typically described as "Give discomfort management." In lots of solutions it is a requirement to administer specific anesthetics under protocol, specifically breathed in representatives and some parenteral options through standing orders. While exact drug extents vary by jurisdiction and employer, the core of PUAEME008 supply discomfort management is less concerning the molecule and more regarding safe, effective systems:
- Assessment that separates discomfort as a signs and symptom from pain as a syndrome. A person with crushing upper body pain is not the like a person with musculoskeletal strain. Risk triage for red flags: shock, neurovascular compromise, area syndrome, sepsis, head injury with degrading GCS, and feasible drug-seeking behaviors that can cloud assessment. Analgesic choice matched to mechanism, seriousness, comorbidities, and environment. The "right medicine" depends on whether you have oxygen, tracking, IV accessibility, and the skills to rescue the airway. Monitoring and titration to result, not to habit. Repeat evaluations drive dose decisions and escalation. Documentation that defends your professional thinking and fulfills medicolegal standards.
Successful prospects in a PUAEME008 supply pain administration program reveal that they can apply these concepts under stress, not simply recite them in a classroom.
Where nurses come across PUAEME008
I first completed the device during a shift from ward nursing to blended ED-ambulance work in a country service. We did not have immediate medical cover after hours. Analgesia decisions had consequences, and the nearest tertiary healthcare facility sat 90 mins away along roadways that iced over by twelve o'clock at night. PUAEME008 licensed me to offer breathed in methoxyflurane, titrate fentanyl under procedure, and escalate for ketamine with clinical appointment. That scope will certainly differ, but the framework really felt universal.
Nurses meet this system in 3 primary contexts:
- Pre-hospital or access environments where standing orders call for a proficiency like PUAEME008 to provide analgesia without a prescriber on-site. Emergency departments and immediate treatment centers where nurse-initiated analgesia paths exist. Remote and rural clinics where registered nurses take care of pain throughout long term transport intervals.
Even if your setup maintains analgesic management strictly under clinical orders, the analysis, tracking, and documents elements of the unit boost your method and reduce medical risk.
Competencies you must demonstrate
A great pain administration course that aligns to PUAEME008 will certainly not be a slideshow of medication truths. Anticipate to demonstrate 4 broad expertises:
Clinical evaluation. You will certainly be expected to make use of a validated discomfort scale, but extra significantly you will certainly reveal you can determine the most likely pain device from history and examination. That suggests centering discomfort, mapping radiation, inspecting neurovascular status, screening for warnings, and determining when analgesia must wait for life-saving treatments. For instance, a hypotensive injury individual could need blood products prior to anything else.

Analgesia selection and dosing. You will certainly warrant why a provided client gets a details agent, at a given beginning dosage, with a mentioned strategy to titrate. Blended agents have synergy and compromises. For instance, matching paracetamol and an NSAID lowers opioid demands in several bone and joint injuries, yet NSAIDs are a poor selection for believed crack with bleeding danger or kidney impairment. In a hissing patient with extreme discomfort, ketamine could be more secure than morphine because of its minimal respiratory depression.

Monitoring and acceleration. The system anticipates you to expect restorative result and side effects, to change dosage, to change agents if needed, and to recognize when to call for back-up. Breathed in analgesia might be sufficient for a disjointed shoulder reduction, but a femoral shaft fracture throughout a lengthy transportation might require IV choices and local techniques if available.
Communication and documents. You ought to have the ability to hand over clearly to paramedics, ED coworkers, or a retrieval team. Great paperwork complies with the chain: assessment, decision, drug and dose, action, damaging results, and plan. It is also your shield if a case is reviewed.
Matching training course choices to your role
The discomfort administration courses market is crowded. Names vary, and not every offering associate PUAEME008. When screening companies of discomfort management training programs, try to find these characteristics:
- Nationally acknowledged system mapping that particularly details PUAEME008 supply pain administration, not simply a generic "sharp pain" module. Practical scenarios and simulation with skills sign-off, not only e-learning. If your function includes inhaled analgesia or IV titration, you ought to handle devices and execute simulated application and monitoring. Clear assessment period and re-certification needs. Analgesia competencies normally end after 1 to 3 years, with updates on methods and pharmacovigilance. Trainer qualifications with pre-hospital or ED experience. You desire educators that have actually made these choices at 3 a.m., not only in lecture halls.
Short courses in pain management can be worthwhile if they strengthen the core abilities with hands-on practice. A certificate program hurting management that includes case studies, pharmacology refresher courses, and emergency situation pain administration drills often tends to have the most effective transfer to the floor.
What "great" technique looks like at the bedside
A new graduate as soon as asked why I invested three additional mins collecting background before https://garrettimvb681.fotosdefrases.com/top-discomfort-administration-courses-just-how-puaeme008-boosts-your-abilities giving an analgesic to a patient with ankle joint discomfort. The factor was straightforward. The ankle joint was not the problem. The proximal fibula hurt, the foot was cool, and the individual had pain out of proportion to touch. The differential consisted of a vascular issue, and urgent imaging trumped early NSAIDs. A pain administration certification ought to educate you to calibrate this type of judgment.
When analgesia is appropriate, match the medicine to the job:
- Mild to modest bone and joint discomfort without warnings commonly responds to paracetamol and an NSAID, plus ice, elevation, and immobilisation. Opioids add little advantage when the standard steps are neglected. Severe stressful discomfort on scene may ask for inhaled analgesia as a bridge. It purchases time to develop IV accessibility, splint effectively, and strategy conclusive analgesia en route. Renal colic can favor ketorolac when kidney feature permits, with judicious opioid titration if required. Metoclopramide covers nausea and can aid with opioid sparing. Fracture decrease or misplacement requires preparation: adequate analgesia and muscular tissue relaxation, surveillance, and post-procedure neurovascular reassessment.
Nurses with PUAEME008 expertise are typically the initial to act. The very best ones do not miss the fundamentals of convenience: repositioning, cozy blankets, quiet setting. Those information reduced total analgesic demands, especially in older adults.
Pharmacology you will really use
A discomfort management certification training course hangs around on pharmacology, but memorizing medication charts is not the outcome. You need fluency with the patterns.
Paracetamol continues to be the most safe initial step in most individuals. Dose issues. Adults commonly get 1 g by mouth or IV every 6 hours, conscious of advancing everyday restrictions, liver illness, and malnutrition. It is stackable with virtually every little thing else.
NSAIDs deliver strong alleviation for inflammatory discomfort: strains, kidney colic, dental discomfort, and post-op discomfort when enabled. They are contraindicated or dangerous in GI blood loss, advanced renal disability, improperly controlled heart failure, and late pregnancy. Programs need to cover agent-specific subtleties, like the start and renal influence of ketorolac versus ibuprofen, and when to avoid them in injury with prospective bleeding.
Opioids are devices, not services. Morphine, fentanyl, and oxycodone each have profiles that matter. Morphine brings histamine launch and hypotension danger in some individuals. Fentanyl works quickly, which is beneficial in titration, yet it does not last lengthy. Oxycodone is simple to recommend improperly and easy to taper badly. Breathing depression is the hazard that obtains the headlines, but the more common problems are queasiness, vomiting, bowel irregularity, and delirium in older grownups. PUAEME008 training emphasizes titrate-to-effect application and rigorous pain management certification course monitoring.
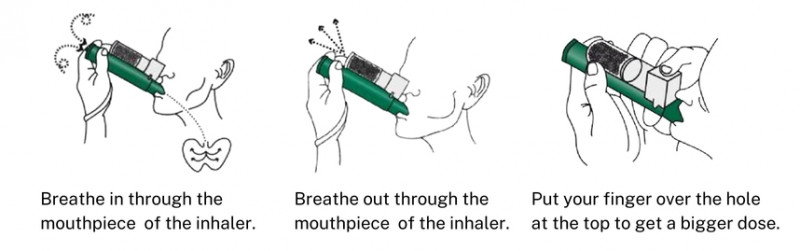
Inhaled analgesia such as methoxyflurane is common in pre-hospital and minor treatment setups. It is patient-controlled and fast to begin, though restricted by collective dose ceilings and potential nephrotoxicity with prolonged or duplicated usage. You require to recognize exactly how to advise people, ensure ample air flow in constrained areas, and recognize when the inhaler masks hypoventilation or hypoxia.
Ketamine has taken a niche in emergency pain monitoring for serious trauma, burns, and opioid-tolerant people. Sub-dissociative dosing gives analgesia with marginal breathing clinical depression, but hypertension, tachycardia, and emergence reactions can occur. It requires tracking and training, which several pain monitoring training courses now include.
Regional blocks are progressively component of nurse-led procedures in some solutions, especially femoral nerve obstructs for hip cracks monitored by innovative practitioners or physicians. If your extent includes this, your certification course hurting management need to cover clean and sterile strategy, composition, safety and security checks, and documentation.
Adjuvants such as antiemetics, antispasmodics, and neuropathic representatives are the difference in between chasing pain and managing it. Little details aid. An early dose of ondansetron commonly stops the cycle of vomit, missed analgesic, boosted pain, and even more opioid need.
Safety webs and side cases
Two populaces will examine your training: older grownups and those with compound usage disorders.
Older adults have reduced physiologic gets and numerous medications. Kidney feature may be marginal even if creatinine looks normal. Start with non-pharmacologic steps and paracetamol if proper, stay clear of long-acting opioids, and screen for ecstasy. I have viewed a next-door neighbor's hip fracture patient drift right into complication after what felt like a conservative opioid dose. The resolution was time, fluids, family members presence, and a mindful switch to set up non-opioid analgesics.
Patients with opioid resistance or a history of abuse need clear, compassionate treatment. Do not conflate under-treated discomfort with drug-seeking behavior. Confirm background, use unbiased findings, and communicate a strategy. Short-acting, titratable opioids with close tracking are frequently much safer than high preliminary doses or long-acting formulas. Involve addiction medicine early if available. Your documentation ought to mirror assessment, reasoning, and agreements made.
Other side cases consist of maternity, where NSAIDs are commonly restricted in the 3rd trimester, and the use of nitrous or methoxyflurane requires obstetric input. Asthmatics may not tolerate specific NSAIDs. Head injuries deserve special caution with sedating anesthetics that cloud neuro checks. PUAEME008 training need to motivate you to consider these threats before you draw up a syringe.
How training courses examine abilities, not just knowledge
Most discomfort management courses for nurses that map to PUAEME008 make use of a blended format. Anticipate pre-reading on pharmacology, multiple-choice expertise checks, and, most importantly, scenario-based assessments. You could take care of a mock compound fracture on a manikin, guide a standardized person via inhaled analgesia, or run a situation of extreme stomach pain with evolving vitals. Assessors view your sequencing, communication, and paperwork. Time stress is part of the style. That is suitable, given that the device targets emergency discomfort management.
A fair program likewise consists of debriefs that contrast different safe approaches. For instance, one candidate might choose fentanyl titration after inhaled analgesia, an additional could prioritize a local block if a clinician is present to support it. Both can be proper if the thinking and surveillance are sound. Good facilitators do not teach "one right method," they instruct a collection of secure options matched to context.
Documenting pain like a professional
If a case mosts likely to audit or coronial review, the quality of your discomfort documentation will get on screen. Right here is a succinct pattern that has actually stood more than years in ED and pre-hospital settings:
- Record the baseline pain score with context: place, personality, radiation, triggers, and function. "Discomfort 8/10, sharp, best flank to groin, colicky, worse with motion, nausea or vomiting present." Justify your strategy in one sentence. "Provided most likely renal colic, begin ketorolac if kidney function permits, plus ondansetron, reassess 10 minutes, take into consideration fentanyl titration." Document the drug, dose, course, time, and simultaneous treatments like splinting or ice. Reassess at specified intervals. Tape-record both subjective pain scores and objective indications: facial expression, guarding, heart rate, respiratory system rate, and practical examinations like ability to deep breathe or move the limb. Note damaging effects or lacks thereof, any type of dosage adjustments, and the handover or discharge strategy, consisting of warnings regarding driving, added dosages, and red flags.
Your notes are part of your discomfort monitoring certification at work. They reveal medical maturity and shield you and your patient.
Choosing between general and role-specific training
There is worth in both wide discomfort monitoring training and concentrated, role-specific programs. A general discomfort monitoring qualification course constructs pharmacology and evaluation skills that equate throughout setups: ED, wards, aged care, and neighborhood. Role-specific PUAEME008 provide discomfort administration training courses concentrate on emergency methods, standing orders, and the logistics of analgesia in less controlled environments.
If you split your time in between ED triage and ambulance support, take the role-specific course first. If you are early in your profession or returning from a leave, begin with a more comprehensive pain administration certification program to refresh basics, after that include PUAEME008 for scope.
Pain monitoring training courses for physio therapists likewise exist, commonly stressing non-pharmacologic methods, placing, and rated exposure for chronic discomfort. Interdisciplinary sessions where registered nurses and physio therapists train together can be eye-opening. You see how language and activity can lower pain scores without a solitary milligram of medication.
Common mistakes and how to stay clear of them
Three mistakes turn up repetitively in audit meetings. The very first is under-treatment due to be afraid of opioids or an uncertainty. People bear in mind when their discomfort is rejected. If your analysis sustains it, deal with early with secure representatives, monitor carefully, and document the plan.
The second is over-reliance on a solitary medication, especially opioids. Well balanced analgesia is generally better. Combining paracetamol and an NSAID, including ice or splinting, and using antiemetics lowers the overall opioid requirement and adverse effects. Think in combinations.
The 3rd is bad communication. If you titrate analgesia, your coworkers require to recognize what you have actually done and just how the patient responded. Handovers that consist of the trajectory of discomfort and function help the following group proceed securely. "Discomfort from 9 to 6 after 50 mcg fentanyl, able to exist still for CT, respiratory price steady at 16, strategy further 25 to 50 mcg if pain surges over 7, take into consideration ketamine if additional boluses required."
Turning proficiency into habit
Competency is granted on a day, but ability matures over time. Develop 3 practices to keep your PUAEME008 sharp:
- Treat discomfort as an essential indicator plus a tale. Ask the client what an effective result appears like. For some, it is resting without waking; for others, it is walking to the bathroom. Audit on your own. As soon as a month, examine a handful of your instances for time to first analgesia, overall dosages, negative effects, and person remarks. Patterns emerge. You will certainly see where you continually under-dose or overuse an agent. Rehearse the side instances. If your solution enables it, run tabletop drills: extreme burns with limited IV accessibility, senior hip crack with ecstasy, pediatric fracture with panicked moms and dads. Confidence grows when you exercise outside of crises.
Where PUAEME008 fits within broader specialist growth
A discomfort administration qualification is one sounded on a ladder. After you understand it, consider broadening into sedation expertises, injury treatment, or regional anesthetic in partnership with medical coworkers. The content you discover here additionally boosts persistent pain discussions. Clients notice when a nurse describes why paracetamol and an NSAID, taken on schedule, will assist them relocate physio tomorrow, and how movement feeds back to lower discomfort. That is the clinical loop that decreases readmissions and enhances satisfaction.
For supervisors, sustaining discomfort management training for registered nurses is a safety and security investment. When team can examine and deal with early, time to imaging reduces, treatments go smoothly, and complaints regarding being overlooked decrease. A well-structured provide discomfort management course likewise creates a common language throughout changes and disciplines. You will certainly hear it in handovers.
Final thoughts from the floor
I have offered analgesia in a well-lit resus bay with complete monitoring and in a roadside ditch with rain blowing sideways. The principles did not alter. Assess initially, match medication to system and risk, titrate with intent, and interact the plan. PUAEME008 formalizes those practices and offers you the legal and professional scaffolding to act decisively.
If you are considering discomfort management accreditation, pick a carrier that maps cleanly to the system, pushes you in reasonable circumstances, and offers sensible responses. If you currently hold the credential, keep utilizing it deliberately. Discomfort is complex. Individuals remember who took it seriously, and your skill can be the distinction in between a distressing memory and a workable one.